Professional
-
October 23, 2026
SilverSense SDF is a 38% silver diamine fluoride solution used professionally to help arrest caries and manage dentinal sensitivity. It is supplied in a 5 mL dropper bottle, with approximately 0.03 mL per drop.
Once the client and lesion have been assessed and SDF has been selected, the application itself is straightforward.
1. Isolate, Clean and Dry
Isolate the affected tooth, then clean and dry the treatment surface.
Remove accessible plaque and debris so the lesion is visible and the site can be adequately dried.
Cotton rolls or rubber dam may be used for isolation, and the IFU also notes that petroleum jelly or cocoa butter may be used to help protect gingival tissues.
2. Dispense
Dispense 1–2 drops into a disposable Dappen dish.
Each drop contains approximately 0.03 mL, and this amount may treat up to 5 sites per client.
SilverSense has a blue tint to improve visibility i
-
October 21, 2026
The caries risk assessment is complete. The lesion has been assessed. The indications point to SDF as an appropriate treatment option.
Now it is time to set up.
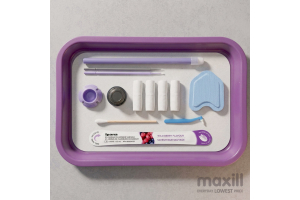
SDF application itself is simple, but the armamentarium around it matters. A thoughtful setup helps the clinician control the material, maintain a dry field, improve visibility and reduce the risk of unintended contact or staining.
The broader clinical workflow remains:
SCREEN. DISPENSE. ISOLATE. APPLY. PROTECT.
But once SCREEN is complete, the chairside setup begins with gathering the right armamentarium.
Start With the Setup Surface
Before dispensing SDF, think about what is sitting between the material and the operatory counter. SilverSense SDF can stain countertops, floors, instruments, clothing and skin brown or black. The Canadian Instructions for Use specifically caution clinicians to avoid spills and
-
October 19, 2026
Silver diamine fluoride (SDF) is an effective, minimally invasive option for managing active carious lesions. It is simple to apply, requires relatively little chairside time, and can be especially valuable when conventional restorative care is difficult, delayed or not immediately feasible. Evidence-based clinical guidance supports 38% SDF as a nonrestorative treatment option for appropriate carious lesions. (Slayton et al., 2018)
Yet SDF still appears to be under-integrated into routine clinical care.
The bigger question may no longer be:
“Does SDF work?”
It may be:
“Are we identifying the right clients for it?”
That is why SDF should begin with caries risk assessment — not with the bottle.
SCREEN. DISPENSE. ISOLATE. APPLY. PROTECT.

-
September 09, 2026
In 2022, Health Canada updated its recommendations for radiation protection in dentistry through Safety Code 30. One of the notable changes pertains to the use of lead aprons during dental X-ray procedures. While lead aprons have traditionally been a standard protective measure, the new guidelines suggest that their use is optional in certain scenarios. However, the use of thyroid collars remains a critical requirement. This article delves into the rationale behind these changes, the decision-making authority regarding protective measures, and the importance of individualized client care in dental radiography.
Lead Aprons: Optional Use in Routine Dental X-rays
According to the revised Safety Code 30, the routine use of lead aprons for clients during standard dental X-ray procedures is no longer deemed necessary, provided that all other recommendations for
-
August 26, 2026
If you’ve ever walked into a sterilization area or supply room and noticed sterile instruments stored in the lowest drawer, bottom cabinet, or on a shelf near the floor, you’re not alone. This is one of the most common “it seems fine” storage habits in dental settings, especially when space is tight.
But here’s the truth… storing sterile instruments at ground level increases risk, even if the instruments are wrapped, even if they’re in a closed drawer, and even if they “aren’t technically touching the floor.” This isn’t just a rule for the sake of rules. It’s a practical, evidence-based risk reduction control that protects sterility, improves workflow, and reduces avoidable reprocessing. Let’s break it down.
The Simple Truth: The Floor Zone Is the Highest-Risk Zone
In every healthcare environment, including dental operatories and sterilization rooms, the floor is where contamination accumulates. That’s because the floor is constantly exposed to:
-
July 29, 2026
Quarantining instruments after sterilization is an important safeguard in dental practice. Holding instruments until sterilization monitoring results are available, especially biological indicator results, helps prevent the premature release of a failed load.
However, quarantine on its own is not an instrument traceability system. It is one part of a larger system.
Quarantine answers one question: Can this sterilization load be released?
Traceability answers a broader and more defensible question:
Can we prove which instruments were used, on which patient, from which sterilizer and load?
That distinction matters.
Quarantine Is a Release-Control Step
Quarantine is a holding process. It keeps instruments
-
July 15, 2026
For many years, dental offices have used the foil test as a simple way to check whether an ultrasonic bath was producing cavitation. The process was familiar: place a piece of foil into the ultrasonic cleaner, run the cycle, and look for pitting, marks, or perforations in the foil as a sign that the unit was functioning.
However, current Canadian reprocessing standards have moved beyond this method.
As outlined in CAN/CSA-Z314:23, Canadian Medical Device Reprocessing in All Healthcare Settings, under Clause 11: Decontamination of reusable medical devices, ultrasonic cleaners shall be tested using commercial methods that verify cleaning and functionality daily when the ultrasonic cleaner is used. The standard also notes that foil testing is not a validated testing method.
-
July 01, 2026
Running a dental practice takes more than strong clinical skills, it requires effective communication. From the front desk to the operatory, the way we talk with each other can either build trust and efficiency or create unnecessary tension. One communication style that empowers both leaders and team members is solution-based communication.
What is Solution-Based Communication?
Solution-based communication is a way of speaking and listening that focuses on outcomes and collaboration, rather than blame or dwelling on problems. Instead of pointing fingers or getting stuck on what went wrong, the conversation turns toward what can be done to improve the situation.
Think of it as shifting from:
“Why did this go wrong?”
to
“How can we make this work better next time?”Why It Matters in a Dental Office
Dental teams are unique: hygienists, assistants, dentists, and administrators
-
June 17, 2026
Instrument reprocessing is intended to follow a linear, one-way workflow. The process moves from contaminated to clean, then inspected, packaged, labelled, sterilized, cooled, inspected again, and stored. Each step prepares the item for the next step, and the workflow should not move backward once the item has progressed forward.
For this reason, labelling belongs before sterilization. The label is part of packaging and load preparation. It connects the package to the sterilization record, including the date processed, sterilizer used, load or cycle information, and the individual responsible for packaging. Once the package has been sterilized, the focus is no longer to “work on” the package; it is to protect the sterile barrier, allow the package to cool, inspect it, and store it appropriately.
The expected workflow is:
-
June 02, 2026
I started using the term ‘Learning Dodger’ a few years ago when I began to notice a pattern among some dental professionals. They weren’t disengaged entirely, and they weren’t necessarily poor clinicians, but something was missing. They avoided growth opportunities, skipped over new ideas, and resisted updating their knowledge. I didn’t know what to call it at first, but the phrase dodging learning seemed to fit.
It’s also a concept I wrestle with personally. As someone currently completing a BA in Adult Education, I can’t get enough of learning, I’m always looking forward to my next “educational fix.” For me, growth feels energizing, not exhausting. So when I encounter professionals dodging learning, I find myself both curious and concerned. Why would someone resist something that fuels so much professional pride and purpose?
Dentistry and dental hygiene are professions rooted in science, technology, and evidence-based care. From infection prevention to new p